
Thirteen years, one patient, one mitochondrial variant: what a Leigh-like case shows about the limits of a DNA answer
Edited by Samael A. Tejada, Founder & Editor-in-Chief
·Tip: press play, then lock your phone or switch apps — the article keeps reading.
A 13-year case report (Frontiers in Genetics, November 2, 2026) tracks one patient with the complex I variant MT-ND4 m.11470A>C at 51.8% heteroplasmy in saliva, from optic atrophy at age 3 to respiratory failure at 16. Despite a 0.9 deleterious-prediction score and no nuclear-gene alternative, the variant formally remains a VUS — an instructive limit of genetic answers in mitochondrial disease.
Mitochondrial genetics runs on percentages: the same variant can be harmless at a low share of a person's mitochondrial genomes and devastating at a high one. This case is the fullest record yet of one such variant — and its authors refuse to call it proven. That refusal is the most useful part of the paper for anyone holding a genetic report of their own.
What happened over the thirteen years?
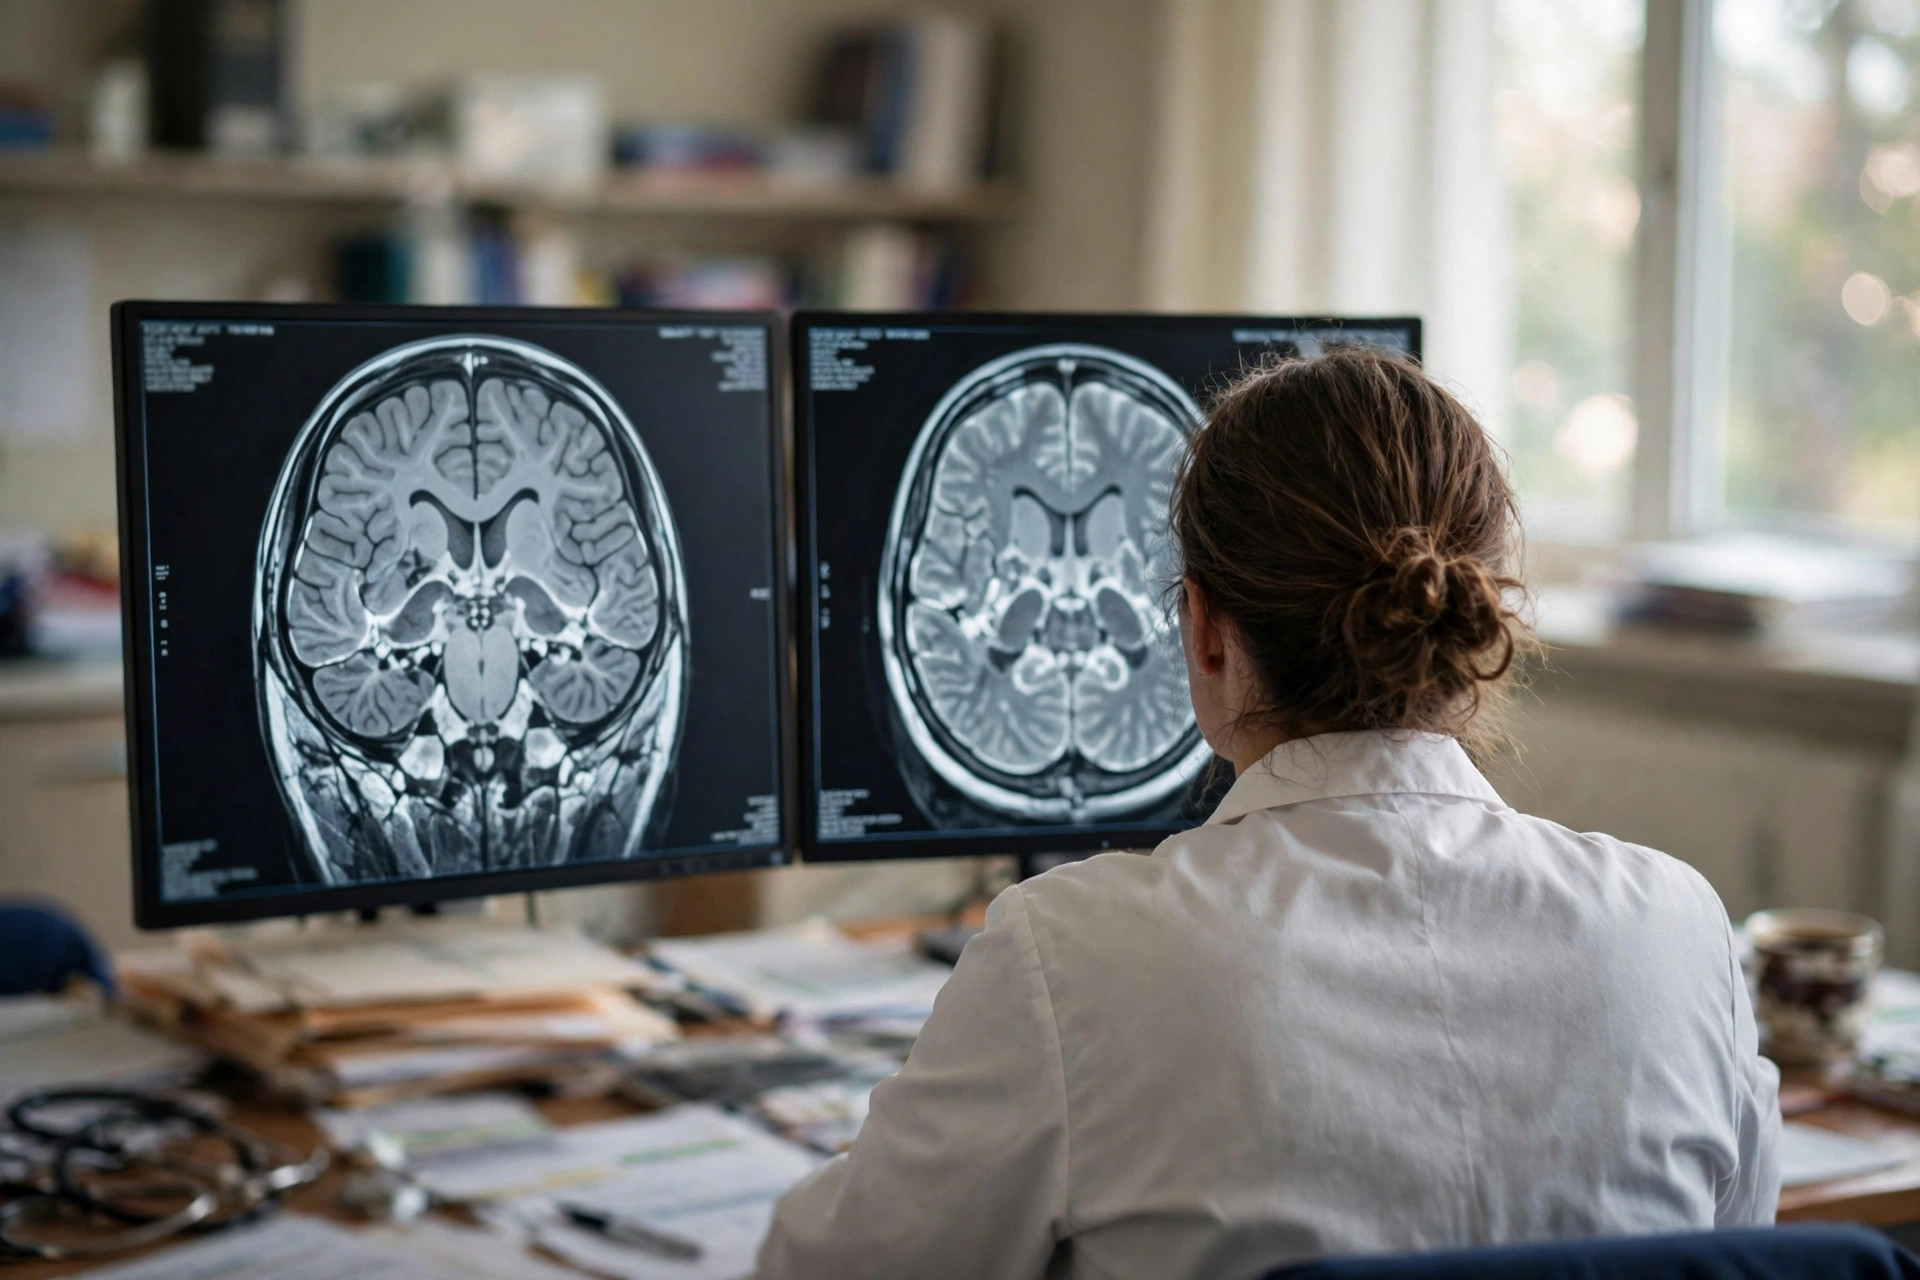
The timeline is the contribution. Onset at age 3 with strabismus and optic atrophy; a slow progression of limb weakness, gait instability and dysarthria through childhood; then, at 16, bilateral MRI lesions in the basal ganglia, thalami, midbrain, pons and medulla oblongata — the deep brain structures Leigh syndrome classically strikes — followed by respiratory failure, intubation and 11 days of invasive ventilation. He improved during that admission: strength recovered from grade 4 toward 4+/5, lactate normalized from 1.52 to 0.98 mmol/L, and at three-month follow-up his Barthel index was 65 and he was walking independently at home. The team notes it cannot determine whether the mitochondrial cocktail given during admission contributed to the improvement. The embedded literature review — PubMed searched October 14, 2026; 359 records screened — had previously linked this same variant to MELAS and to a Leigh syndrome record in a pediatric cohort, so this case widens the variant's reported spectrum rather than introducing it.
What does 51.8% heteroplasmy actually mean?
Each cell carries many copies of the mitochondrial genome, and heteroplasmy is the percentage carrying a given variant — here, a pipeline-reported 51.8% of reads in a saliva sample (the lab's detection limit was about 25%). The variant changes lysine 237 to asparagine in ND4, a membrane subunit of complex I, at a residue conserved across the 12 species the team aligned and described as a charged component of the proton pathway complex I uses to pump protons. The variant was not detected by Sanger sequencing in saliva from the patient's mother or his dizygotic twin brother, and deep mitochondrial sequencing covered the genome completely (mean depth 15,848.91x) while exome sequencing covered 20,858 nuclear genes at 127.27x mean depth without finding an explanatory nuclear variant. APOGEE 2, an ensemble predictor built for mitochondrial variants, scored this one 0.9 on a 0-to-1 deleterious scale. That is a substantial circumstantial case — and the authors still grade it insufficient, because none of it measures what the variant does to complex I in an affected tissue.
Why does the variant stay 'uncertain' after all that?
Because the formal system asks for kinds of proof this case cannot supply. Reassessed under mtDNA-adapted ACMG/AMP rules, m.11470A>C earned only PM2_Supporting (it is rare) and PP3_Supporting (computational prediction) — leaving it a variant of uncertain significance. The authors state the gaps plainly: no functional evidence demonstrates the variant impairs complex I activity; heteroplasmy was measured in saliva at one time point and cannot be extrapolated to brain or muscle, the tissues that matter; the family declined further tissue testing for financial reasons; and with no biochemical mitochondrial abnormality demonstrated, the full diagnostic criteria for Leigh syndrome were not met — the honest label is Leigh-like. For readers, the transferable lesson is the shape of a strong case report: a decade-plus trajectory, deep sequencing, family testing, prediction scores — and a conclusion that still says 'associated,' not 'caused.' A consumer genetic report that says less than this deserves even more caution.
Frequently asked questions
What is heteroplasmy?
The percentage of a person's many mitochondrial genome copies that carry a particular variant. In this case the MT-ND4 variant was measured at 51.8% in saliva. Higher shares in energy-hungry tissues generally mean stronger effects, but a saliva percentage cannot be extrapolated to brain or muscle.
Did the variant cause this patient's illness?
It has not been proven to. After formal reassessment the variant remains a VUS — a variant of uncertain significance — because there is no functional evidence it impairs complex I, even though the clinical picture, prediction score of 0.9, and absence of a nuclear-gene explanation are consistent with it.
What is a VUS?
A variant of uncertain significance: a genetic change whose connection to disease is not established under formal criteria. A VUS is not a diagnosis, and it should not by itself drive treatment decisions.
Where the evidence stands
- Established: MT-ND4 encodes a membrane subunit of mitochondrial respiratory complex I; heteroplasmy — the share of mitochondrial genomes carrying a variant — shapes whether and how mtDNA variants cause disease; and Leigh syndrome is a genetically heterogeneous mitochondrial disorder typically marked by bilateral deep-brain lesions.
- Preliminary: In a single-patient 13-year longitudinal case (Frontiers in Genetics, Nov 2, 2026; DOI 10.3389/fgene.2026.1969094), MT-ND4 m.11470A>C at 51.8% saliva heteroplasmy accompanied a Leigh-like course from optic atrophy at age 3 to respiratory failure at 16, with an APOGEE 2 score of 0.9, no explanatory nuclear variant on exome sequencing, and absence of the variant in mother and twin.
- Contested: Causality itself: after mtDNA-specific ACMG/AMP reassessment the variant remains a VUS (PM2_Supporting + PP3_Supporting only), with no functional evidence of complex I impairment and heteroplasmy measured only in saliva, as the authors themselves state.
Join the discussion
To get the conversation started: What questions does this story raise for you? Share them below — every comment is reviewed by our moderators before it appears.
Community discussion only — not medical advice. Every comment is reviewed by our moderators before it appears. Sign in with Google or a free Hyvor account to join in.